The minute health systems started shutting down services at the start of the COVID-19 pandemic, reality hit that something was broken.
It was more than the supply chain, which forced the rationing of personal protective equipment. It went beyond cleaning protocols as facilities tried to mitigate infection spread. It was greater than a need for more ICU beds and negative pressure rooms available to treat infected patients.
It was everything, from surge capacity to traffic flow, technology to staffing, The strain of closed clinics and operating rooms proved to be greater than many had anticipated, and coupled with overtime for other staff, and expenses for quick room conversions for negative air flow, the situation elicited one large question: “How did we get here?”
For more than a decade, the planning for healthcare organizations has been guided by the Institute for Healthcare Improvement’s Triple Aim – to improve the experience of care, population health, and the cost associated with care. That pursuit of the aim led to campuses and facilities that are more intuitive for patient-families, more efficient for staff, and more cost effective to operate…all in normal operations.
While an understatement, COVID-19 proved to be anything but normal, and in its sweep across the nation, it exposed a deficiency in our collective healthcare system. Missing from the Triple Aim was “resiliency,” a word often applied to physical structures, not so much to operations. As organizations pursued the Triple Aim, with a strategic and structural shift from inpatient to outpatient care, facilities and campuses reflected that shift, designed for consumers of care with a focus to keep the community healthy and reduce the need for hospitalization.
The flood of need for hospitalization in the pandemic isn’t an indictment that the previous pursuits were wrong. Rather, in exposing the gaps in healthcare operations, the pandemic has revealed the need to evolve our planning approaches. More than answering how organizations got here, the question is, “How do we move from here?”
A New Planning Approach
The scenario laid out by the pandemic is that: a scenario. On its own, COVID-19 represents a national event whose scale and impact has little precedent. However, in the past 15 years, the coronavirus spread is one of many unplanned events that have challenged both large and small organizations, alike. MERS, SARS, mass shootings, 100-year floods, tornadoes – the scenarios that strain the resources of hospitals, clinics, and the communities that they serve occur at a greater frequency that ever before.
Through that lens, we can both critique the plans that put organizations where they are now and evolve the process to find a resilient path to managing through these scenarios. Simply called Scenario Planning, this new approach to the traditional master planning process aims to mitigate the impacts scenarios can have on operations and facilities.
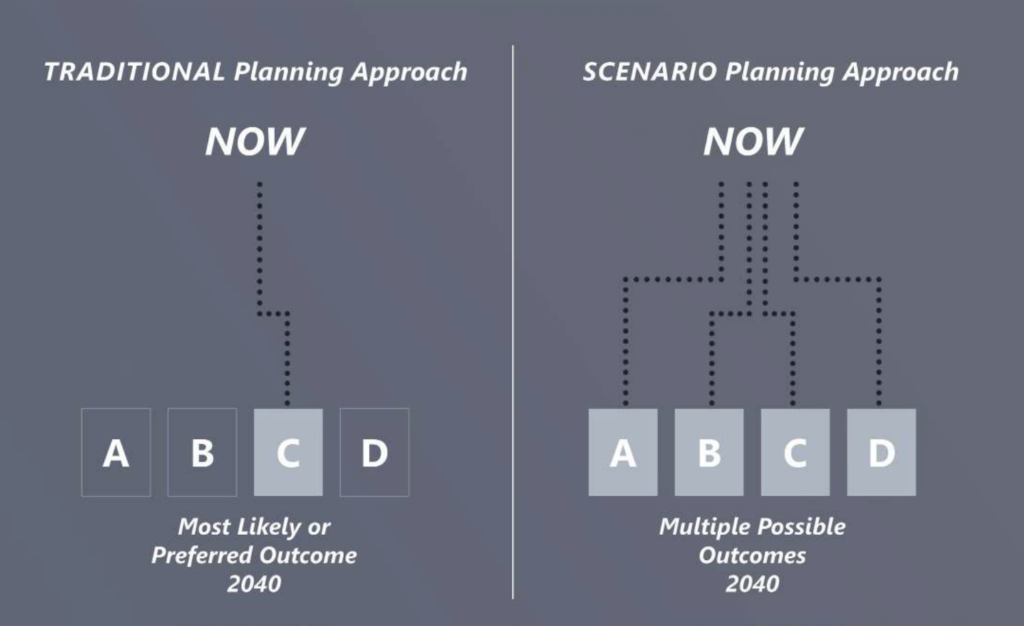
Most campuses and facilities have been programmed through a master planning process, a practice that usually relies on observed trends to forecast a probable future. What the current pandemic has shown is that the scenario under which the plans are crafted focus on a desirable future, one predicated that the future will be similar to the past. The master planning process often assumes an environment that operates business as usual, and the facilities and infrastructure are designed accordingly.
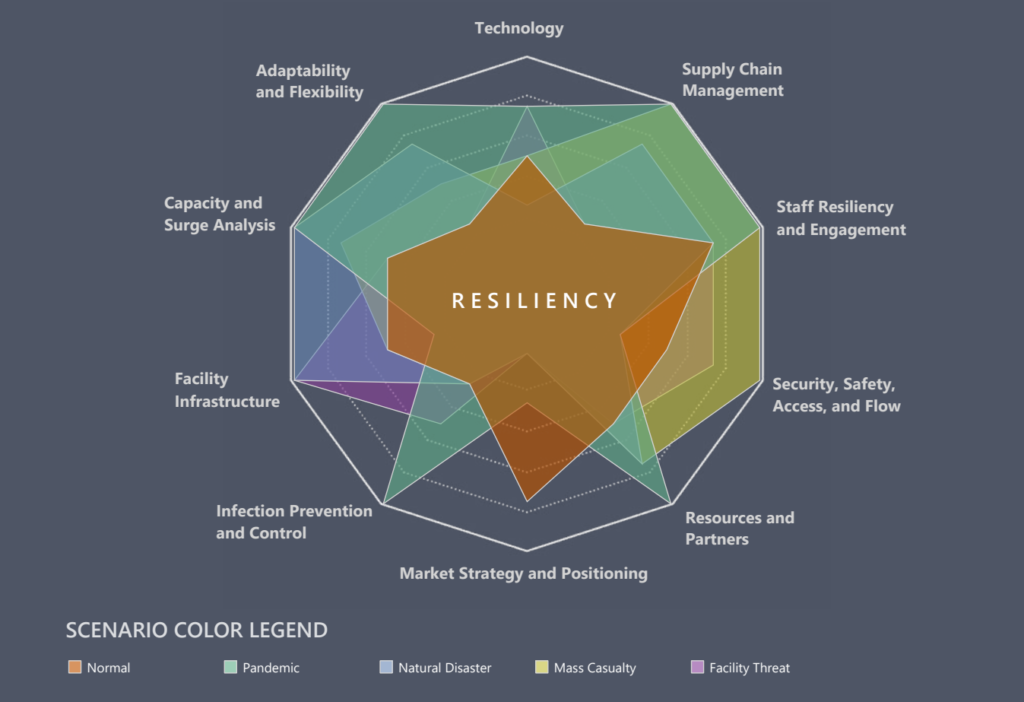
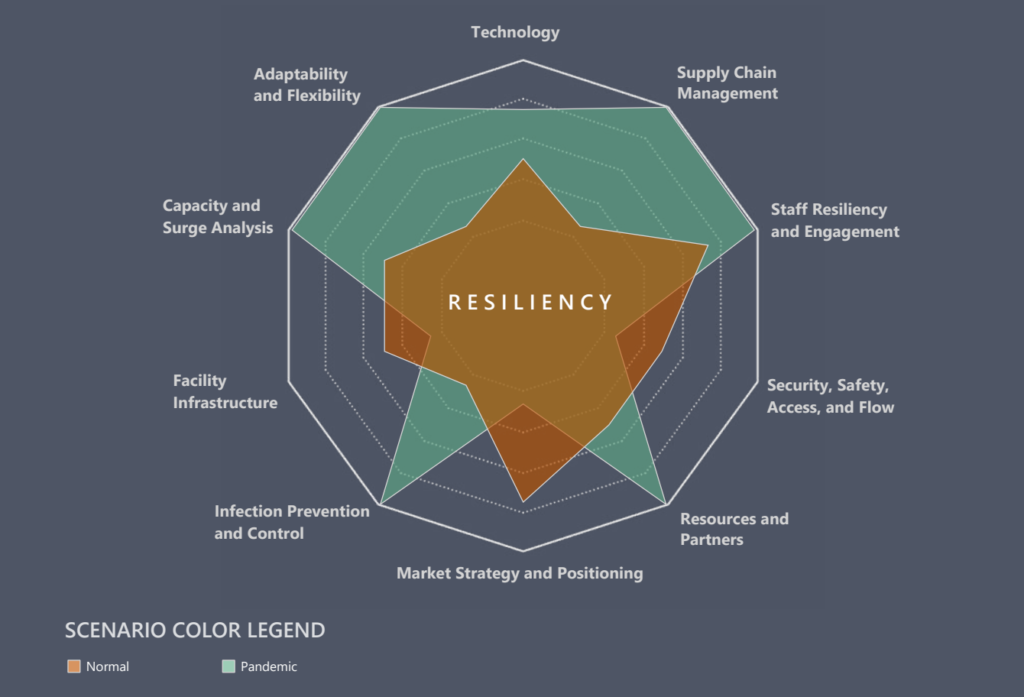
Scenario planning takes the planning process to a new level. More than planning for a worst-case scenario, scenario planning puts the integrity of an organization’s operations at the center of the planning process. A dynamic approach to planning, the planning process enables organizations to understand the possible effects unplanned, adverse events could have on their personnel, supplies, and facilities.
Where vision drives much of the master planning process, scenario planning complements that vision through a segmented analysis of the drivers of an organization’s operations. By studying the impacts scenarios have on each part of an organization’s operations, the organization is forced to consider enterprise-wide how it can respond to adverse conditions demanding rapid attention and adaptation. Beyond the response, the analysis concentrates the planning on how organizations can pivot facilities, technology, and personnel in a moment while protecting its ability to operate at optimum levels.
Resiliency Redefined
Scenario planning combines the vision of where organizations want to go under controlled conditions with an approach that examines that resiliency of the vision in the face of uncontrolled conditions. It takes the idea of resiliency in operations to expand its definition beyond recoverability. Instead of analyzing how quickly a normal state of operations can return after those operations are disrupted, scenario planning allows teams to consider how well the organization can absorb a disruption to maintain continuous operations.
Facilities and infrastructure are then designed for disruption absorption – alternative care sites, alternative care delivery methods, flexible mechanical systems, adaptable spaces, alternative traffic flows, as well as support for staff wellness under unrelenting stress. By creating a dialogue between all the various parts of an organization, a dynamic plan is shaped to help organizations maintain the integrity of their operations through adversity.
According to a report from the American Hospital Association, shuttered and modified operations in response to COVID-19 has resulted in a 19.5% drop in inpatient volumes at non-federal hospitals, and an additional 34.5% drop in outpatient volumes. Losses from the first four months of the pandemic plus projected continued losses, even after services come back online, are expected to exceed $323 billion in 2020. (Click to read the report.)
The current pandemic represents a real existential threat for many healthcare organizations. The look of hospitals, clinics, and their operations after the pandemic will be different from what it was before the pandemic. However, “different” must be “better.” While COVID-19 provides a better understanding of how a pandemic can impact operations, it is only one of many scenarios that force organizations to deviate their operations from normal. Disruptions to operations will continue. Only through a better planning process can we mitigate the impacts those disruptions can have on the integrity of the whole healthcare organization.
Mike Boldenow is a principal at BWBR who has spent much of his career working with healthcare organizations to develop facilities that enhance the services they provide in both small communities and large metropolitan regions. Mike can be reached at [email protected] or 651.290.1996. Scott Holmes, RA, ACHA, LEED AP, is a retired principal and healthcare planner who has worked with organizations from large health systems to critical access hospitals to program spaces that increase efficiencies and improve the delivery of care.
A nationally registered historic lab and classroom facility at Carroll University has earned LEED® certification, making it the second campus facility to attain LEED certification in two years.
Rankin Hall’s 26,500-square-foot renovation completed the third and final phase of a BWBR-designed campus capital plan to improve academic spaces focused on science and health programs. Previous phases included Carroll University’s first LEED certified project, Hastad Hall, which also features Waukesha’s first green roof, and Jaharis Science Laboratories.
The renovation includes nine classrooms and labs, 25 faculty offices, three new psychology testing rooms to perform research, and additional open, flexible spaces that inspire a collaborative learning environment.
The project focused on using historically appropriate, environmentally friendly, long-lasting materials and design strategies. Those included clay tile roofing, zinc flashing and downspouts, and a low-VOC historically appropriate paint palette. Energy efficiency and indoor environmental improvements were made with sensitivity to the historic masonry and wood structure. Strategies included spray foam insulation added in the roof joints, LED lighting, and new systems for heating and cooling, in addition to refinishing the wood floors.
The original wood windows were removed, restored, and then replaced to maintain the historic character of the building from both the inside and outside. New insulated windows were installed on the outside of the original windows. These windows were thermally broken, with low-e coating and argon fill. To maximize the ability to see the original windows from the exterior of the building, the window frames are as narrow as possible with low iron glass for extra clarity.
Rainwater run-off from Rankin Hall is directed to bioretention ponds built as part of the Jaharis Science Laboratories project. Moving beyond LEED, an added exterior ramp, new elevator, and gender-neutral bathrooms improved the building’s accessibility and inclusivity.
“The ability to reuse and improve existing structures is a key sustainability strategy. The historic nature of Rankin Hall made LEED certification a welcomed challenge,” said Sara Curlee, AIA, LEED AP, senior project architect at BWBR and the project’s LEED project administrator. “Rankin Hall’s design helped to set the tone for the campus aesthetic more than 100 years ago, and it’s gratifying to see the facility continue to reflect that tone while influencing future generations of students in a safe, accessible, and sustainable environment.”
Named for Carroll University’s second president, Rankin Hall, located in a National Historic District, is listed on The National Register of Historic Places and the Wisconsin Register of Historic Places, and is designated as a City of Waukesha Landmark. In 2019, the project received the George Gunn Award for Excellence in Architectural Preservation and Historic Restoration by the City of Waukesha Landmarks Commission.
With 40 LEED accredited professionals currently working at BWBR, the firm is one of the leading advocates for sustainable high-performance design, incorporating green design strategies into complex environments like academic facilities, R&D centers, and hospitals. As part of a global movement to design smarter, BWBR is a signatory to the AIA 2030 Commitment which challenges architects and engineers to make buildings carbon-neutral by 2030.
When a patient attacks a nurse, there is more than physical trauma that occurs. The consequences of the violence can manifest in anger, fear, anxiety, shame, blame, and post-traumatic stress disorder symptoms that can have negative effects on patient care and job satisfaction (Stevenson, Jack, O’Mara, & Legis, 2015) For the health care organization, aside from the legal ramifications of patient-on-staff or patient-on-patient aggression, such actions can adversely affect staffing, retention, and quality of care.
The reality of care in a mental health center is that it comes with both physical and emotional challenges. A 2011 review of 128 studies across 11 Western nations found that 33 percent of patients admitted to mental health care facilities engaged in aggressive or violent behavior (Bowers et al, 2011). A 2015 meta-analysis found 17 percent of patients on acute mental health units committed at least one act of violence, while 75% to 100% of nursing staff in surveys reported experiencing violence (Iozzino, Ferrari, Large, Nielssen, & de Girolamo, 2015), although researchers noted a lack of a consistent definition of violence across the many studies they researched. A Canadian study of registered nurses in psychiatric centers found 55 percent reported physical or emotional abuse by patients; more than 20 percent reported physical abuse in their last five shifts (Stevenson et al., 2015). In addition to the short- and long-term disability costs associated with the aggression, the abuse can cause a fear of patients that influences unit policies and procedures, and ultimately the freedom of all patients.
Until recently, most of the research on reducing aggression in mental health settings has concentrated on improving patient assessment tools and staff training. However, a growing body of research is shifting the focus to environmental stressors that can exacerbate patient anxiety and emotions. As Ulrich and colleagues noted in the Journal of Environmental Psychology, “Crowding is the only environment-related variable to receive attention in multiple studies of aggressive behavior in psychiatric wards” (Ulrich, Bogren, Gardiner, & Lundin, 2018, p. 54). These researchers hypothesized that evidence-grounded stress-reducing features could possibly reduce incidents of aggression in psychiatric facilities. Experience suggests that not only is that possible, it can go further to improve the environment in which care is delivered.
From Command and Control to Human-Centered
Mental illness presents one of the greater challenges in health care, because treating a mind in crisis is different than treating a body in crisis. When patients presents for psychiatric care, they are often in a state in which their world is out of proportion and no longer rational.The environment into which they are admitted can either amplify the illness or provide a calming space to support care.
Past approaches to designing for mental health treatment have traditionally focused on a command-control model that uses rules and regulations to modify or mandate expected behaviors. Reasons for this can vary, but a primary driver was that addressing the risk patients pose to themselves and others in their mental state often overshadowed addressing their needs (Antonysamy, 2013). The resulting environments were sterile at best, with little to engage the patient on a personal level. Or, at worst, they were nearly correctional, with barriers between staff and patients, and few elements to help patients find dignity and a proper sense of reality. In addition to promoting interpersonal safety, operational strategies that prioritized ligature prevention to mitigate patient self-harm would produce care settings that treated the patient as a threat.
The problem with these practices is that they either failed to establish or else eroded trust between the patient and care team. Anxieties heightened. Resentment between patients and staff became more probable. Instead of promoting healing, the environment almost worked against it.
Human nature is such that people respond to their environment before they respond to rules. Take road design, for example. Remote Texas highways that are often long and straight, and appear wide open, invite a self-prescribed driving speed no matter what speed limit is posted. On a winding country road along the Mississippi River, with curves and small tunnels, the speed limit is easier to adhere to because the design elements in the environment encourage such adherence. It’s understandable. It makes sense.
The same can be said for architectural design. Because human nature is to respond to the environment, we can design settings that encourage a certain type of behavior, rather than forcing rules that demand such behavior. This is the genesis of the Human-Centered Safety approach, using design elements upstream in the care setting to avoid downstream incidents that may require restraints, seclusion, or other responses that patients could interpret as adversarial.
Establishing the Tone of Care
Confrontational. Scary. Threatening. Punitive, Alienating. Humiliating. These words came from a patient focus group in describing the current conditions of a psychiatric care environment scheduled to be renovated. More than unwelcoming, the words evoke a setting that is less than therapeutic, where hope for healing is far from the first thing the patient – and the family admitting the patient – experiences.
While not representing the quality of the care most psychiatric staff provide to patients, the words often are an image representing the first impressions people have of the physical environment they see: harsh fluorescent lighting illuminating a long, narrow corridor of rooms with closed doors; a heavy steel, windowless entry door with signs demanding the relinquishment of personal belongings; a nurses’ station behind shatterproof glass with a pass-through for patients to hand over personal items; patient rooms with muted colors lacking any elements to humanize the experience; and an admission sequence that can hide the patient, through corridors that aren’t daylit and/or that expose the mechanical and plumbing conduits servicing the facility.
The problem with this first impression is that it conveys a sense that the patient can’t be trusted. It leaves the person in the midst of a mental health crisis wondering, “What are they going to do to me?” And it leaves the family admitting the person, especially if that person is a child or adolescent, wondering if they are making the right choice for their family member.
Details communicate messages – locked doors, hinges, windows at the end of a long hallway. As past design practices evaluated the details with an eye toward safety, durability, and ligature prevention, they often overlooked what those details, like a doorless bathroom, would communicate to the patient. The upstream approach to safe design shifts that conversation. Rather than safety through restriction, it promotes safety through therapy, leveraging the first impression of the facility to establish a healing tone. See Figure 1.
Inviting. Liberating. Comforting. Therapeutic. Approachable. Dignified. Contrasted with the previous set of words, these provide a different spectrum through which design details can shape the care environment: skylights and solar tubes to flood spaces with daylight without creating glare; warm colors and tones to comfort patients in their rooms; beds positioned away from corners to help patients feel unrestrained; curved window benches to allow patients a place to cocoon and feel protected (see Figure 2); zonal floor patterns to help patients transition from perceived personal spaces to safe communal settings; soft and clustered furniture to promote socialization; and views of, if not access to, nature, communicating a sense of empowerment and beauty and, thereby, hope. Even material choices like flooring that feels natural instead of indestructible can turn what patients and families describe as a “walk of shame” into a “walk of hope.”
Figure 1. Adolescent inpatient unit with welcoming nurses station; soft, durable furniture; personal zones; and open environment to facilitate healing outside of the patient’s room.
Figure 2. Patient room in an adolescent inpatient unit, with bench seating at window providing connection to natural light.
Addressing Spatial and Social Density
Details that help calm a patient at the start of the admission process address the fight-or-flight response that can grip a person in a mental health crisis. Other details can address the stressors that can raise the patient’s level of anxiety or agitation once on a unit and when adverse confrontations occur. Ulrich and colleagues note that while there is ample research examining the relationship of crowding to aggressive behavior in psychiatric wards, many of the studies fail to explicitly define density; mix the term “crowding” with ward density, patient density, or space; or look at crowding through bed occupancy rates (Ulrich et al., 2018). The problem is that “across studies in psychiatric facilities there is no consistent association between crowding defined as high ward occupancy and aggression/violence” (p. 54). Ulrich writes that what is known through studies of other high-density environments, from prisons to apartment buildings, is that the number of persons in a room (social density) is an important variable, while personal space (spatial density) is only a factor when space per person becomes restricted.
The unique aspect of inpatient psychiatric care environments is that the most effective care occurs outside the patient’s room, making the unit’s communal spaces a critical component of the care protocol. Thus, the value of the space goes beyond the cost per square foot, with an emphasis on managing both spatial and social density to promote a healing environment and mitigate behaviors that could be detrimental to that healing.
For most individuals in most cultures, personal space is a radius of 2 to 4 feet. However, for people experiencing a mental health crisis, that personal space may be much larger, with people who have experienced trauma needing even greater distance behind their backs. In a unit design that places a nurses’ station in a position to monitor corridors from multiple directions, the space through which traffic flows can become pinched, increasing the spatial density at that particular point no matter what the unit census is. Any intrusion into the personal space of a patient who is standing at that spot can trigger an adverse response. The same is true for long, narrow corridors. For an alternative design, see Figure 3.
Figure 3. Transition unit with open nurses desk and sight lines.
Spatial density also influences the design of individual spaces. Beds located in the corner of the room can make the patient feel boxed in. Chairs in a group therapy room can raise someone’s level of anxiety if there is space behind the chair for others to approach from the back. Pushing the furniture to the walls of group therapy rooms opens the space, literally and socially, especially when arranged in a manner that communicates a more equalized relationship, such as a semi-circular shape (See Figure 4).
Addressing social density shapes a space that helps patients seek privacy and regulate their relationships with others. Where previous designs may have accommodated 18-20 beds on psychiatric units, this census level proved hard to manage, especially for patients with high acuity. Modern design leans toward units with 8-10 beds, and some as low as 2-4 for the most acute patients. Spaces such as sensory rooms give patients a place of refuge where they can recompose when they feel their anxiety levels rising (See Figure 5). Small bench seats outside the entrance to patients’ rooms gives them a way to transition gradually into a more social setting, while still finding comfort in the proximity of their rooms. Movable furniture rather than fixed or weighted furniture in common areas also gives patients the ability to control their physical spatial relationship with others and to avoid stressors such as noise or arguments.
Figure 4. Activity lounge in in-patient mental health unit.
Figure 5. Sensory room with user-chosen LED lighting.
Giving Patients Choice and Control
Addressing aggression through the lens of density goes beyond census population to include factors such as acoustics, air movement, lighting, and even odors. Sound and light, especially, can play an important role in patients’ behavior; highly reverberant spaces can play a triggering role that can be exacerbated by long corridors, contributing to perceptual distortions (Karlin & Zeiss, 2006). Poor or dimly lit spaces can affect both patient mood and the perceptions of the space as safe and nurturing.
Improving lighting usually includes ways of bringing natural light into the unit, an effective strategy especially for patients with depression or bipolar disorders. Skylights and solar tubes that light spaces without creating glare or silhouettes are not only effective strategies for incorporating daylight, but they provide a secondary benefit of increasing workplace satisfaction and reducing workplace stress (Joseph, 2006).
Lighting solutions are not limited to natural lighting, though, and this has opened new avenues of calming strategies for patients. In a study of children with autism in educational facilities (Long, 2010), incandescent lamps and light fixtures with dimmer controls were found to provide a calmer environment through warm lighting and the sense of control the students felt they had over the space.
Examples of Outcomes
Leveraging Long’s findings (2010), a renovation of an inpatient mental health unit in Minnesota for children and adolescents incorporated light dimmers, accent lighting, and even music control panels in many of the activity, therapy, and group rooms. In a six-month study of the unit, patients were asked to rate the features that they felt were most calming. Of the top five listed, four of them were amenities that allowed them to control the environment. Specifically mentioned were the sensory room, colored LED lighting in shared spaces, and music and dimmable lighting in patient rooms (Trzpuc et al., 2014). In that same study, 87% of staff described the overall environment as having a very or somewhat positive impact on patient behaviors, and 86% describe the unit as having a positive impact on staff interactions with patients.
After a renovation of a secure mental health unit in a state-operated security hospital incorporated many of the daylighting, furniture, and group therapy amenities outlined in this article, a first-year report of staff injuries, lost work time, and medical claims saw a significant drop from the previous two years, with recordable staff injuries falling more than 30%. The security hospital recorded its lowest rate of recordable injuries in 11 years, marking the first time the unit had dropped below the national average in seven years.
Conclusion
Many elements can influence safe operations of an inpatient psychiatric unit, including some not fully explored in this article. From access to outdoors and activities that engage muscles and motor skills, to staff culture, creating an atmosphere of trust with patients and feelings of hope and wellness depends on more than one strategy. However, design strategies demonstrate that “the physical environment in which that culture and philosophy exists can be one of the greatest tools of its symbolic expression” (Bailey, 2002, p. 25).
Coming out of an age when design strategies upholding safety in an inpatient psychiatric center meant erecting barriers between patients and staff and/or overusing restraints and seclusion, our understanding of how people respond in a state of crisis is changing how we see the delivery of care they seek. Once seen as counterintuitive, eliminating those physical barriers and opening connections between staff and patients is elevating safety by eliminating the psychological walls that kept patients from feeling trusted and respected. By recognizing the human need to have choice and a sense of control in a world that feels out of proportion, health-care organizations can shape an environment that is warm and welcoming. In that environment, safety is promoted through dignity.
References
Antonysamy A. (2013). How can we reduce violence and aggression in psychiatric inpatient units? BMJ Open Quality; 2:u201366.w834.
Bailey, K. (2002). The role of the physical environment for children in residential care. Residential Treatment for Children and Youth, 20(1), 15-27.
Bowers, I., Stewart, D., Papadopoulos, C., Dack, C., Ross, J., Khanom, H., et al. (2011). Inpatient violence and aggression: A literature review.Report from the conflict and containment reduction research programme. Institute of Psychiatry, Kings College London
Iozzino, L., Ferrari, C., Large, M., Nielssen, O., & de Girolamo, G. (2015). Prevalence and risk factors of violence by psychiatric acute inpatients: A systematic review and meta-analysis. PloS one, 10(6), e0128536. https://doi.org/10.1371/journal.pone.0128536
Karlin, B. & Zeiss, R. (2006). Environmental and therapeutic issue in psychiatric hospital design: Toward best practice. Psychiatric Services, 57(10), 1376-1378
Stevenson, K.N., Jack, S.M., O’Mara, L., & Legis, J. (2015). Registered nurses’ experiences of patient violence on acute care psychiatric inpatient units: an interpretive descriptive study. BMC Nursing 14, 35,. https://doi.org/10.1186/s12912-015-0079-5
Trzpuc, S., Wendt, K., Heitzman, S., Skemp, S., Thomas, D., & Dahl, R. (2016). Does space matter? An exploratory study for a child-adolescent mental health inpatient unit. HERD: Health Environments & Research Design Journal, 10(1), 23-44.
Ulrich, R., Bogren, L., Gardiner, S., & Lundin, S. (2018). Psychiatric ward design can reduce aggressive behavior. Journal of Environmental Psychology. 57, 53-66.